
What is an Achilles Tendon Repair?
When the Achilles tendon has completely ruptured (see Achilles Tendon Rupture), it can be treated with surgery to stitch the torn ends together, or without surgery in a special boot. For most people both give similar results, so the choice is made with your surgeon. If surgery is chosen, the frayed edges are stitched back together. Several different operations can be done, but the most common uses an open cut over the tendon.
You should expect to be in rehabilitation for a number of months after the operation (about three, but this varies). In the early recovery period your leg will be in a special ‘equinus’ cast that stops the tendon re-rupturing. Within two weeks, most people can begin using a cam walker boot and eventually careful weight-bearing with crutches.
The usual total rehabilitation is between six weeks and several months. You should expect to need some physiotherapy and/or exercises, and to avoid your usual high stress activities for several weeks. Running and restarting sport are generally not possible until about four to six months after the operation (this also varies between people).
The operation is generally very effective and rarely has major complications such as massive bleeding. Some people do re-rupture their tendon and need further treatment. Most people are very happy with their long term results and eventually return to their normal exercise program.
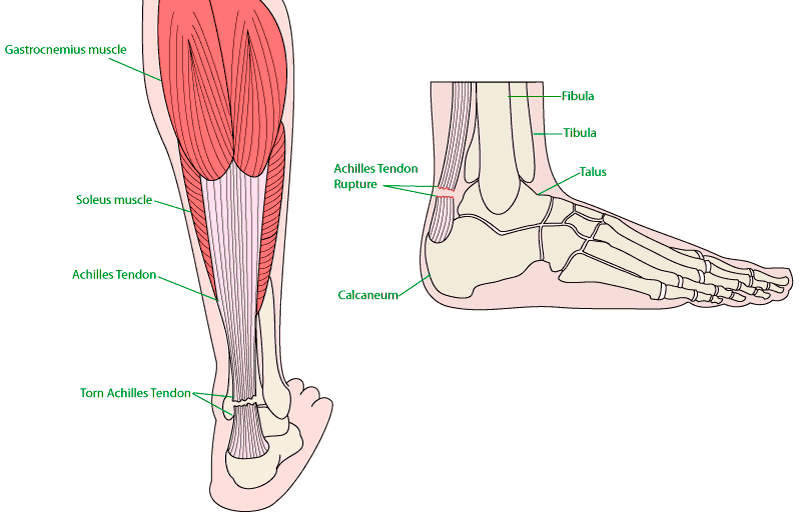
Who is this operation for?
This operation is for people who have a full-thickness rupture of the Achilles tendon, and/or when less invasive treatment (such as casts and physiotherapy) has failed.
An Achilles tear that is more than 4 weeks old is called a chronic tear. If there is a big gap in the tendon, a piece of tendon from elsewhere may be needed to bridge it.
What are the benefits of the operation?
This surgery is usually very effective. Most people have no noticeable long term change in function, provided rehabilitation is completed.
Risks of not having the surgery
Intensive physiotherapy with splinting or orthotics is a very reasonable alternative to surgery. In many cases, non-operative and operative treatment have similar long term results.
Surgery does carry a lower risk of re-tearing the tendon. It is also often recommended for people with high demands on their ankles, including athletes, especially runners. The downside is that surgery has several risks, including infection and nerve injury. These are usually minor, but they are not negligible.
As is often the case in orthopaedics, the decision to operate is made case by case. You should discuss your options and any concerns with your physiotherapist and surgeon.
Who should not have this surgery?
The major concern with this surgery is infection, so people at higher risk (for example people with diabetes and long term smokers) may be advised against surgery.
However, your surgeon has a lot of experience with this issue and can discuss the benefits and risks with you.
Complications
Complications following repair of full-thickness rupture:
- Skin injury. The skin over the Achilles tendon can become strained by long term swelling. This can lead to skin breakdown that needs more treatment from a podiatrist, the local doctor or, rarely, a surgeon.
- Sural nerve injury – the sural nerve gives sensation (touch) to a patch of skin on the outer side of the foot. Injury to this nerve can cause tingling or numbness in that area.
- Re-rupture of the tendon & tendon necrosis. Necrosis means death of tissue. The Achilles tendon has a somewhat vulnerable blood supply, and necrosis of the tendon is an unfortunate but rare complication of rupture.
- Achilles tendinitis and/or pain.
- Infection – this can occur deep in the ankle or in the skin.
- Deep vein thrombosis (DVT) – clots in the large veins of the leg are a well-known result of long periods of immobilisation. In hospital the doctors use preventive measures, including heparin and TED stockings, to stop these clots forming.
There are a number of other risks involved in any surgery. For more information on these, see Complications of Surgery.
Before the operation
Before you reach hospital, you can apply ice to your ankle and keep it raised. Pain relief from the chemist can also help.
Emergency Department | Preadmission Clinic
If you have a sudden rupture, you will probably be in so much pain that you come to the emergency department. The staff can assess whether you are safe to have surgery and arrange an operation.
If your rupture happens gradually over time, you will be seen at the Preadmission clinic to make sure you are fit for the operation and that all the tests you need are done.
During the visit, you will be seen by a
- doctor
- nurse
- anaesthetist (if necessary)
Tests
Tests that may be ordered for you include:
- Ultrasound scan of your ankle.
- In rare cases, more sophisticated scans like MRI are needed.
- If your doctor is concerned about the possibility of a fracture, you may have X-rays.
Other tests that are used to assess whether you are fit for surgery include:
- Blood tests
- X-ray of your Chest
- Urine Test
- ECG
Preparing Your Skin
Your skin should have no infections or irritation before surgery. If it does, contact your orthopaedic surgeon for a program to improve your skin first.
Tip
Carry a list of your medicines with you, with the name, dose and how often you take each one.
Medications
Your treating team will tell you which medicines to stop and which to keep taking before surgery.
Get some help from your friends and family
Although you will be able to walk with crutches or a walker soon after surgery, you will need some help for several weeks with tasks such as cooking, shopping, bathing and laundry. If you live alone, your orthopaedic surgeon’s office, a social worker or a discharge planner at the hospital can help you arrange for someone to help at home.
About the Operation
Repair of the Achilles is a fairly short operation, usually under 1 hour. It is generally very safe, with few major complications.
Minimally invasive repair – in this method, the surgeon makes a short cut along the back of the heel and opens the skin. The tendon can then be reached easily, pulled back into place and the free ends stitched together.
When the free edges of the tendon are badly frayed, your surgeon may need to tie the threads together in a knot. This should not be visible or painful or affect function, but you may be able to feel it above your heel.
If the rupture is very severe, your surgeon may need to reinforce the damaged Achilles. This usually means taking a small piece of tendon from the sole of your foot and grafting it onto the Achilles.
Your surgeon will then carefully replace the paratenon over the repaired tendon. This is a thin covering that supplies the tendon with nutrients and speeds healing.
The scar from this approach is small but visible. The advantage of this method is that the results are generally very good.
Percutaneous repair – in this method, the surgeon makes a number of small incisions in the skin and sews the tendon together ‘blind’. While the cosmetic result of this approach is usually better than minimally invasive repair, there may be a higher risk of sural nerve injury (see complications), though other risks, like infection, may be reduced.
After the Operation
When you wake up after your operation, your ankle will be held still in an equinus cast (toes pointing down) to protect the stitches.
If your doctor is satisfied you are safe, you can usually go home without spending the night in hospital. The nurses will make sure you have enough pain medicine to keep you comfortable.
You will need to return to your hospital to have the ankle and the incision evaluated by a nurse or surgeon. If everything is going well, your cast will be replaced by a hinged brace. In most cases, you cannot take any weight (complete non-weight-bearing) through the leg for 4 weeks. This means you will be hopping on your other leg, so as not to take weight on your affected foot. A Physiotherapist will show you how to do this safely with crutches.
Recovery and Rehabilitation
Your ankle will only recover to normal with physiotherapy. So follow your physio’s exercises as closely as you can.
During rehabilitation you may have ongoing pain and swelling. This should ease quickly over time, but you can help by:
- Keeping your leg raised as much as possible. When sitting, put your leg up on a chair so it is at least level with your hip. At night, sleep with several pillows under your foot.
- Occasionally applying ice to your foot.
- Simple over-the-counter medications like Panadol can also help.
If your ankle or leg suddenly becomes red and swollen, or you develop a fever you should see your GP.
The long rehabilitation needed after Achilles repair can be very frustrating, especially for very active people. Even so, discuss any extra exercises you want with your physio rather than striking out on your own at the gym. The Achilles tendon is needed for normal walking, let alone running, and your physiotherapist can advise you on when it is safe to continue.
The First Month
In the first six weeks after your operation, your tendon is very fragile. During this time you must not:
- Flex (‘dorsiflex’) your foot. This stretches your tendon and can cause re-rupture.
- Allow anyone to move your foot around, or force your foot beyond what is comfortable for you.
- Put ANY weight on your foot until recommended by your physiotherapist or surgeon.
- Apply heat or perform intense massages on your ankle.
In this early period of rehabilitation you will gradually begin to put weight on the foot, and your physiotherapist will teach you stretches that increase your flexibility.
- Weight-bearing. Your surgeon will tell you when you can start. Your physiotherapist will show you how to walk with crutches and, when you are ready, how to carefully carry some of your weight on your foot.
- Range of motion exercises. Your physiotherapist will show you exercises that help build strength in the tendon and stop your muscles wasting. You will need to practise these at home.
- You must not flex your foot beyond the level your physiotherapist suggests. Most physios allow you to bring your foot to a 90 degree angle with your leg, but you must not pull your foot up beyond this point because the tendon may be over-stretched.
- Exercises for the rest of your body. While you avoid putting weight on your ankle, your other muscles, especially the large thigh muscles (quadriceps), start to waste. To prevent this, your physio will show you exercises to keep the rest of your body fit and strong. This may involve going to a gym and using a stationary bike.
During this period the incision over your heel forms a thick scar as it heals. It usually becomes smaller and paler over time.
You should have a follow-up appointment with your surgeon within the first two months after surgery. They can discuss your progress and decide whether you are ready for the next phase of rehabilitation.
The First Three Months
Once your surgeon is satisfied your tendon is strong enough, you can move on to more advanced flexibility and strengthening exercises, and increase the weight you put through your foot. You will still need a cam walker boot or other protection.
- Weight-bearing. During this time you will move from walking with crutches to walking fairly normally.
- Strengthening exercises.
- Range of movement exercises. Your physio may now recommend you flex your foot further than before. This helps stretch the healing tendon. By the end of this period you should have full range of motion.
- Proprioception excerises to help you regain balance.
Your physio may recommend large elastic bands to stretch your ankle. You will also start using stairs to improve your ankle.
By the end of this period you should feel able to walk normally. After this, exercises will focus on rebuilding strength in your leg.
The First Six Months
Once your physio and surgeon think you are ready, you can gradually start to run. It is very important not to push yourself harder than you can tolerate when you begin. At this point both your muscles and your Achilles are at risk of injury from the long period of reduced activity.
F.A.Q.s | Frequently Asked Questions
What are the alternative treatments to having a Achilles Tendon Repair?
It is possible to avoid surgery by placing the injured ankle in a cast for a long period of time. However, this does not return the full strength and function of the Achilles. It does however avoid complications like infection and bleeding.
When can I return to sports?
This varies with the severity of the rupture, but most people can begin light jogging at 3 months and return to sport at about 6 months. The same can be expected from surgical and non-surgical management.
During this period your physiotherapist will gradually change the frequency and type of exercises you do. If you are returning to sport, you may also need to practise functional exercises.
These exact timeframes will vary and will be decided by your physiotherapist and surgeon.
When can I return to driving?
You must be free of pain and able to do an emergency stop. This also depends on which foot was operated on (right or left). If you had left sided surgery and drive an automatic car, you may be able to drive 2 to 4 weeks after surgery.
What should I do if I have a problem?
If you have severe pain, a lot of swelling, inflammation or discharge from the incision, tell your GP.
If you cannot contact your GP you should contact the Emergency Department at your local hospital.
References
- Maffulli N, Bartoli A, Sammaria G, Migliorini F, Karlsson J, Oliva F. Free tendon grafts for surgical management of chronic tears of the main body of the Achilles tendon. A systematic review. Knee Surg Sports Traumatol Arthrosc. 2023, 31(10), 4526-4538. PMID 37193823.