
Osteoarthritis is a condition where the joint cartilage slowly wears away over time. Joint cartilage is a smooth, slippery surface that lets the joint move easily.
Osteoarthritis most often affects middle-aged and older people. But it can also affect young people if the cartilage was damaged, such as in an injury.
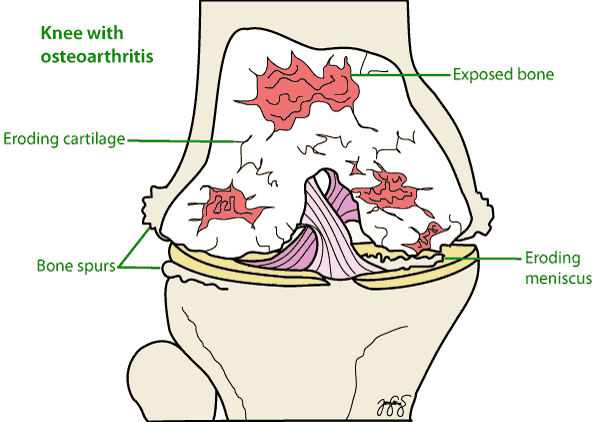
Symptoms
The main symptom you may have is a deep aching pain in your joint which is worse on movement. Other things you may notice are:
- Your knee looks red and swollen
- Your knee feels stiff, especially in the morning
- A grinding or crunching sound when you move your knee
- You may notice your legs look bowed/curved
- You may get a limp
- You may feel your knee locks or buckles
Symptoms vary a lot, from very mild in some people to severe in others
Causes
It builds up over many years, so it is mostly seen in older people. However, there are some factors which cause it to occur early:
- Acute knee injury. This includes trauma to the knee which causes damage to the cartilage
- Knee conditions. Such as rheumatoid arthritis and gout which damage the cartilage
- Weight and overuse. Both these place stress on the knee causing the cartilage to wear away
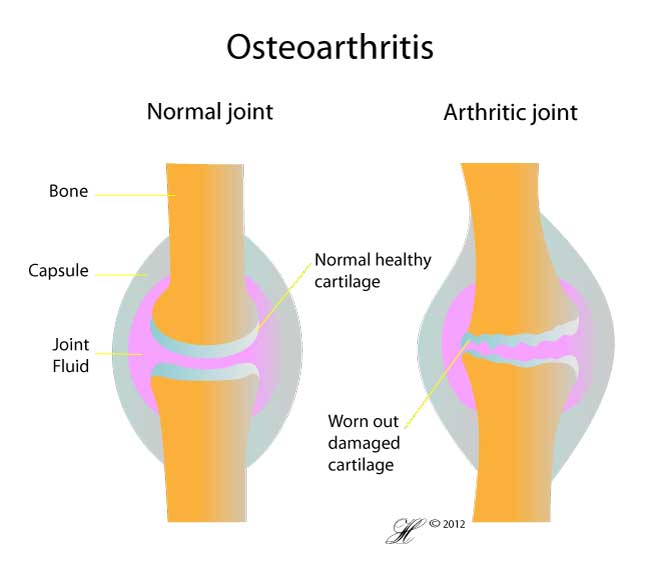
Risk Factors
The risk factors of OA of the knee include:
- Age – The older you are, the more likely you are to get it. In the US one third of people over 65 have it
- Gender – Women are more likely to get it than men
- Weight – Those who are obese are putting more stress on their knees, causing increased wear and tear of the joint and thus more likely getting OA
- Injury – Acute knee injury predisposes to OA
- Shape – a hip or knee that formed or healed out of shape can lead to arthritis earlier
- Work – some jobs raise the risk, such as farming or heavy labour
- Muscle – Weak thigh muscles can lead to OA of the knee
- Knee disease – Conditions like gout and rheumatoid arthritis can predispose for OA
- Vitamins – Low intakes of vitamin D and vitamin C have been linked with higher rates of knee OA
Investigations
Usually your doctor can diagnose your knee arthritis without any investigations. However, an X-ray may be done and this can show a narrowed space between your knee bones which indicates osteoarthritis. Blood tests may be done before surgery. An MRI is rarely needed for knee arthritis. If your knee is swollen with fluid, sometimes it may be aspirated so the fluid can be tested.
Complications
There are a couple of complications that can occur due to OA of the knee. One is deposition of calcium crystals in the cartilage called chondrocalcinosis. OA flares up when there are crystals present, causing increased pain and swelling. Crystals can occur in any joint with or without OA but they are much more commonly seen in a knee with OA. Another complication that can occur due to OA is the formation of cysts behind the knee. These are known as Baker’s cysts. They are soft lumps felt behind the knee which are usually painless but can ache during exercise. These cysts can press on blood vessels causing leg swelling, or the cyst can burst causing pain. Cysts are usually treated by aspiration of the fluid.
Treatment
Osteoarthritis cannot be cured except by replacing the joint, so treatment aims to ease pain and keep you moving.
First measures include weight reduction and pain management with simple pain-killers. Avoid activities which aggravate the knee such as jumping or running and do sports like swimming or cycling. You can see a physical therapist, who can help increase the strength in your legs. You can also use supporting equipment such as knee braces, a walking stick, shoe inserts or energy absorbing shoes.
Your doctor may suggest anti-inflammatory tablets (NSAIDs) or a steroid injection, which can ease pain for a while. Glucosamine is often suggested, but large studies show it helps little.
But if you still have very bad pain and find daily life very hard despite all this, surgery may be an option.
The surgical options available are:
- Knee arthroscopy, which can repair some torn cartilage. It does not help most worn knees, so it is rarely used for arthritis alone.
- An osteotomy which is where your bones are cut to make the knee joint more straight and properly aligned
- A total knee replacement or partial knee replacement where your knee is replaced by an artificial joint
- Cartilage from elsewhere on your body can be grafted into the deficient part of your knee
Knee injections are usually safe, and infection afterwards is rare.
Pain relief from a steroid injection is short term, and repeated steroid injections may harm the joint cartilage.
Many other treatments are promoted for knee arthritis. See Does it work? for what the research shows about exercise, injections, supplements, braces and acupuncture.
Seeking Advice
Your Family Doctor (GP)
Your GP (family doctor) can find out what is wrong and help treat it. Your GP can
- tell you about your problem
- tell you the best ways to treat it
- give you medicine if you need it
- send you to a specialist if you need one
Prevention
Things that can be done to reduce your chance of getting OA
- Maintain your ideal body weight
- Exercise regularly
- Protect your joints by having a good posture
- Avoid repeated stress on your knees
- Listen to your pain, if your knee hurts when you do something, don’t do it
- Avoid direct injury to your knees
F.A.Q. | Frequently Asked Questions
Are osteoarthritis and osteoporosis the same?
No. Osteoarthritis is wear of the cartilage. Osteoporosis is thinning of the bone, which makes it more likely to break.
Does it work?
Does it work? Evidence for knee
What the research shows for treatments people try for knee arthritis, from exercise and injections to knee replacement.
- Does exercise work for knee arthritis? Good evidence it helps.
- Do unloader knee braces work for knee arthritis? Probably helps a little.
- Do cortisone injections work for knee arthritis? Probably helps a little, for a short time.
- Does turmeric work for knee arthritis? Not enough evidence yet.
- Do stem cell injections work for knee arthritis? Not enough evidence yet.
- Does PRP work for knee arthritis? Probably does not help.
- Do hyaluronic acid injections work for knee arthritis? Probably does not help.
- Do glucosamine and chondroitin work for knee arthritis? Probably does not help.
- Does keyhole surgery work for a worn meniscus? Probably does not help.
- Does acupuncture work for knee arthritis? Probably does not help.
- Do wedge insoles work for knee arthritis? Probably does not help.
- Does losing weight help knee arthritis? Probably helps a little.
- Does tai chi work for knee arthritis? Probably helps a little.
- Do NSAID gels and creams work for knee arthritis? Probably helps a little.
- Does therapeutic ultrasound work for knee arthritis? Not enough evidence yet.
- Does knee replacement work better than non-surgical care? Probably helps a little.
- Does ACL reconstruction work better than rehabilitation? Probably does not help, as a routine first step.
- Does robotic knee replacement give better results? Probably does not help, for patient scores.
- Should the kneecap be resurfaced in a knee replacement? Probably helps a little.
- Does a tourniquet help in knee replacement? Probably does not help.
- Does the subvastus approach speed recovery after knee replacement? Probably helps a little, for a short time.
- Does partial knee replacement work as well as total knee replacement? Not enough evidence yet.
- Do cementless knee replacements work as well as cemented ones? Not enough evidence yet.
- Does fish oil work for knee arthritis? Not enough evidence yet.
- Do collagen supplements work for knee arthritis? Not enough evidence yet.
- Does red light or laser therapy work for knee arthritis? Not enough evidence yet.
References
- Bensa A, Piano A, Fumagalli GA, de Girolamo L, Laver L, Magalon J, Sánchez M, Tischer T, Filardo G. Safety profile comparison of intra-articular corticosteroids, hyaluronic acid, platelet-rich plasma, and cell-based injections for knee osteoarthritis. A systematic review and meta-analysis by the ESSKA Orthobiologics Initiative. Knee Surg Sports Traumatol Arthrosc. 2025 Dec 26. Online ahead of print. doi 10.1002/ksa.70230. PMID 41451630.
- Sherman SL, Gudeman AS, Kelly JD 4th, Dimeff RJ, Farr J. Mechanisms of action of intra-articular hyaluronic acid injections for knee osteoarthritis. A targeted review of the literature. Am J Sports Med. 2025, 53(11), 2771-2782. PMID 40108507.
