
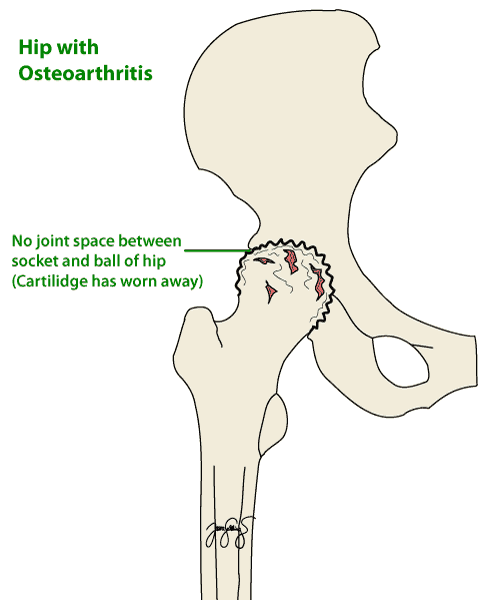
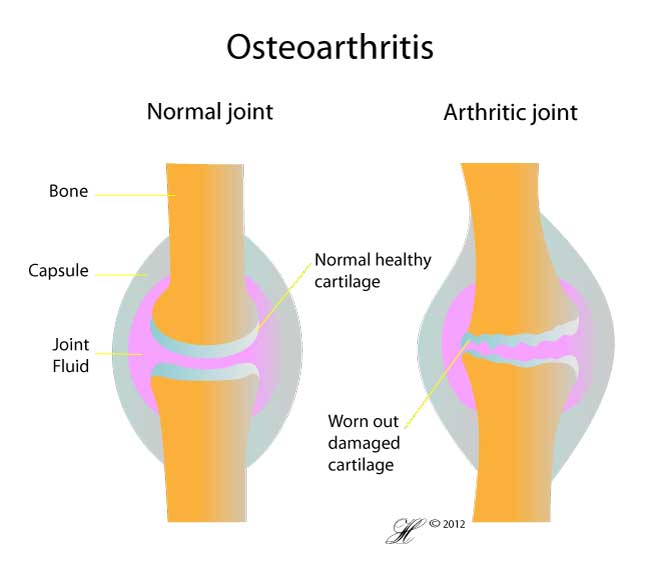
Your hip joint is covered by a smooth and glistening covering called articular cartilage. This cartilage helps your hip move and glide smoothly.
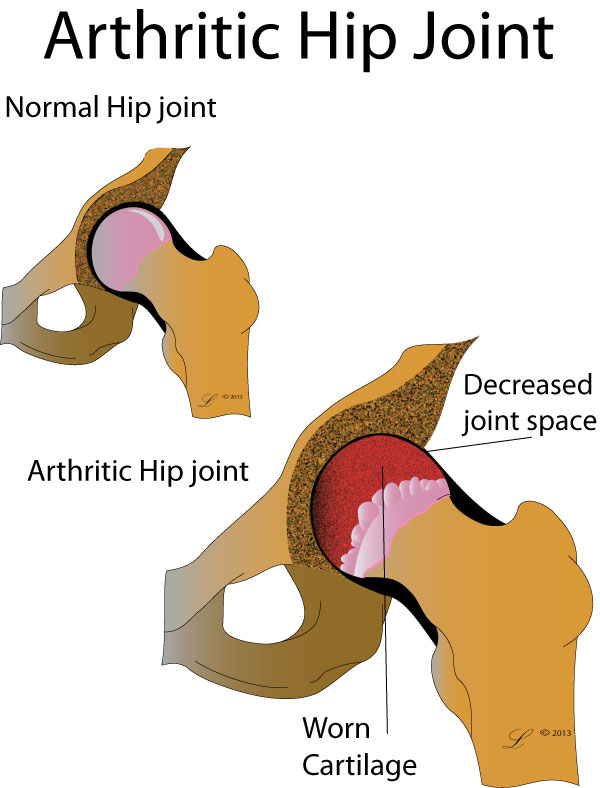
Over time, your articular cartilage can wear away. This is called osteoarthritis and is often referred to as ‘wear and tear’. Over time, the cartilage can break down so much that it no longer cushions the bones.
As well as cartilage break down, bone spurs can form in osteoarthritis which may limit the movement of the joint. This can lead to a stiff and painful hip.
Symptoms
The symptoms of osteoarthritis include:
- Stiffness
- Joint pain
- Muscle weakness
The pain may be felt in the groin, buttock or front of the thigh. It may be worse first thing in the morning but get better with movement and then get worse again towards the end of the day. It is often better with rest.
You may lose the ability to bend or straighten the hip. If the pain is bad enough to limit your movement then the muscles of the hip can become weak.
Causes
The hip is a ball-and-socket joint, and both surfaces are lined with smooth cartilage that lets them glide against each other. In osteoarthritis this cartilage gradually wears away. As it thins, the bone underneath is exposed, the joint becomes rough rather than smooth, and extra bone forms around the edges.
In most people there is no single cause. The wear builds up over many years. It depends on the load the joint has carried, its shape, and your genes.
Some hips wear because of a specific problem, including:
- The shape of the hip itself, where the ball and socket do not fit together smoothly, as in femoroacetabular impingement
- Hip dysplasia, where the socket is shallow and the joint is loaded unevenly
- A previous fracture or dislocation involving the joint surface
- Osteonecrosis, where the blood supply to the ball of the joint fails and the bone collapses
- Inflammatory arthritis, such as rheumatoid disease
- Childhood hip conditions such as Perthes disease or slipped upper femoral epiphysis
Risk Factors
Hip osteoarthritis becomes more common with age, and it often runs in families. Factors that increase the risk include:
- A family history of osteoarthritis
- Older age
- Carrying extra weight, which increases the load through the joint
- Elite-level weight-bearing sport, particularly running
- Work involving prolonged standing, lifting or moving heavy objects
- A previous hip injury, or a childhood hip condition
- The shape of the hip, where the ball and socket do not fit together well
Even without any of these, you can still develop osteoarthritis.
Investigations
The first step of diagnosis is seeing your doctor who will take a medical history. Following this your doctor will examine your hip. Your doctor may move your hip in different directions to check for pain or stiffness.
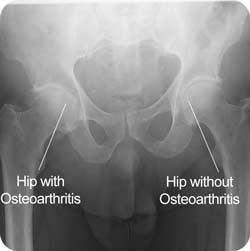
Your doctor may then send you for an X-ray which can show the signs of osteoarthritis such as bone spurs or wearing out of the joint.
Sometimes, a CT scan or an MRI is needed to rule out other causes of hip pain such as:
Complications
Hip osteoarthritis is not dangerous, but as it progresses it can cause:
- Pain that carries on and disturbs sleep
- Increasing stiffness, making it hard to put on shoes and socks or cut toenails
- Walking shorter distances, and losing fitness as a result
- Wasting of the muscles around the hip and thigh
- A limp, and pain in the other hip, the knees or the lower back from walking differently
- The leg feeling shorter as the joint wears
- Low mood and social isolation, where pain limits what you can do
These are reasons to review treatment rather than signs of danger. There is no benefit in waiting until the hip is very stiff before considering surgery.
Treatment
No treatment can undo osteoarthritis. Once the cartilage has worn away, it cannot be replaced. But several treatments can ease pain, keep the hip moving and make daily life easier.
Treatment options are often divided into non-surgical and surgical.
Non-surgical options
- Exercise. Gentle, regular exercise, such as cycling, swimming or water exercise, keeps the joint moving and the muscles strong.
- Physiotherapy can help with improving hip mobility. A physiotherapist can also plan an exercise program that suits how bad your arthritis is.
- Weight loss (if overweight) can help to reduce the symptoms of hip osteoarthritis.
- Walking aids. Using a walking stick in the hand opposite the sore hip can make walking much easier.
- Assistive devices such as hand rails in the bathroom can help with activities of daily living.
- Pain medication can be of benefit in hip osteoarthritis. Paracetamol is safe for most people, but trials show it helps hip and knee arthritis pain only a little. Anti-inflammatory tablets help more, but do not suit everyone. Anti-inflammatory tablets may also help, but check with your doctor that they are safe for you.
A steroid injection into the hip can ease arthritis pain for up to about three months, but the relief usually wears off by six months.
PRP is made from your own blood and can ease pain for a few months. PRP and gel injections have not clearly worked better than a salt water injection.
Surgical options
If the arthritis becomes bad, surgery may be needed to ease the pain and help the hip move better. Operations include:
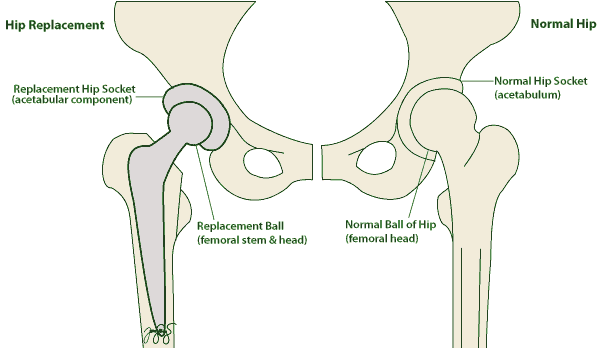
- total hip replacement (also called hip arthroplasty, THR)
- hip arthroscopy
Alternative medicine
Glucosamine and fish oil are often suggested for arthritis. Studies of these supplements have found they help very little.
Often these treatments are expensive, but not necessarily very beneficial. Always talk to your doctor before trying an alternative therapy.
Seeking Advice
Your Family Doctor (GP)
Your GP (family doctor) can find out what is wrong with your hip and help treat it. Your GP can
- tell you about your problem
- tell you the best ways to treat it
- give you medicine if you need it
- send you to a specialist if you need one
Your Orthopaedic Surgeon
Your Orthopaedic surgeon is an expert in treating hip osteoarthritis. He or she will be able to diagnose and treat your hip, whether it is with an operation or not.
Prevention
There is no definitive method to prevent hip osteoarthritis.
Researchers are studying whether some hip shapes make arthritis more likely, such as femoroacetabular impingement.
Hip impingement has been suggested as one possible cause of hip osteoarthritis. In fact, it seems that 1 in 4 people are predisposed to osteoarthritis due to the shape of their hip bones.
In the future, we may have ways to prevent hip osteoarthritis by dealing with the shape of your hip.
No vitamin or supplement, such as fish oil or glucosamine, has been shown to prevent osteoarthritis.
F.A.Q. | Frequently Asked Questions
I’ve heard glucosamine and fish oils might help. Is this true?
Compared with a dummy pill, glucosamine, chondroitin, and the two together do not ease joint pain or slow joint wear. This statement is based on a number of trials that have sought to answer this question.
When is the right time to have a hip replacement if I have advanced OA?
There is no simple rule for when to have a hip replacement. Some people with very bad arthritis on X-ray have little pain and can do most things. Other people with only mild X-ray changes can be greatly affected by their osteoarthritis. When your hip pain limits how you move and stops you doing things you want to do, such as walking, ask your GP about seeing an orthopaedic surgeon. Your surgeon will talk with you about the pros and cons of a hip replacement, and together you can decide if it is right for you.
How long does a hip replacement last?
Most last for many years
What references have been used?
- Primary Osteoarthritis of the Hip: Etiology and Epidemiology. Franklin T. Hoaglund, MD, and Lynne S. Steinbach, MD. J Am Acad Orthop Surg 2001;9:320–327
- Effects of glucosamine, chondroitin, or placebo in patients with osteoarthritis of hip or knee: network meta-analysis. Wandel, Simon; Juni, Peter; Tendal, Britta; Nuesch, Eveline; Villiger, Peter M; Welton, Nicky J; Reichenbach, Stephan; Trelle, Sven. BMJ (Clinical research ed.) 2010 Sep 16. 341;c4675
- Osteoarthritis of the Hip. Nancy E. Lane, M.D. N Engl J Med 2007; 357:1413–1421, 4 October 2007
- Medical management of osteoarthritis of the knee and hip joints. Rebecca Grainger and Flavia M Cicuttini. Med J Aust 2004; 180 (9): 464.
- Epidemiology of hip and knee osteoarthritis. Felson DT. Epidemiol Rev. 1988;10:1–28.
- Reichenbach S, Sterchi R, Scherer M, et al. (2007). “Meta-analysis: chondroitin for osteoarthritis of the knee or hip”. Ann. Intern. Med. 146 (8): 580–90. PMID 17438317.
Does it work?
Does it work? Evidence for hip
What the research shows for treatments people try for hip arthritis, from exercise and injections to the approach used for hip replacement.
- Does exercise work for hip arthritis? Good evidence it helps.
- Does the anterior approach to hip replacement speed recovery? Probably helps a little.
- Does keyhole surgery work for hip impingement? Probably helps a little.
- Do cortisone injections work for hip arthritis? Probably helps a little, for a short time.
- Do hip precautions after hip replacement prevent dislocation? Probably does not help.
References
- Lei T, Wang Y, Li M, Hua L. Clinical efficacy of multiple intra-articular injection for hip osteoarthritis. A systematic review and network meta-analysis of randomized controlled trials. Bone Joint J. 2024, 106-B(6), 532-539. PMID 38821500.
- Lim A, Zhu JB, Khanduja V. The Use of Intra-articular Platelet-Rich Plasma as a Therapeutic Intervention for Hip Osteoarthritis. A Systematic Review and Meta-analysis. Am J Sports Med. 2023, 51(9), 2487-2497. PMID 35971803.
