
What is a Subacromial Decompression?
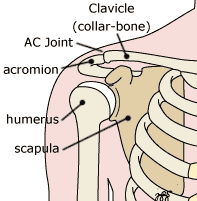
Subacromial decompression, also called anterior acromioplasty, is an operation that removes a small piece of bone from the shoulder. It makes more space for the rotator cuff tendons to glide. It is usually done arthroscopically. This means small cuts are made around the shoulder so a camera and fine instruments can be put in. It is also called keyhole or minimally invasive surgery.
Who is this operation for?
Subacromial decompression is done for people with shoulder impingement who have not improved with non-surgical treatment.
Shoulder impingement is when the rotator cuff tendons do not have enough room to glide freely in the shoulder. The tendons travel through a rigid arch of bone. In people with impingement the arch is too small for the tendons, so they have pain, stiffness or weakness when they use the shoulder. In other words, the bones of the shoulder ‘impinge’ on the rotator cuff tendons. It can affect young and older people, especially those who do a lot of repeated overhead work in sport.
What are the benefits of the operation?
The aim of the surgery is to ease the pain of shoulder impingement. Research suggests the benefit is smaller than many people expect, as explained below.
What does the research show?
Several high quality trials have compared this operation with a placebo operation. In the placebo operation the surgeon looks inside the shoulder with the camera but does not remove any bone. In a UK trial of 313 people, those who had the decompression did no better at 6 months than those who had the camera only procedure.1 A Finnish trial of 210 people found the same at 24 months.2 In the UK trial, both operation groups did a little better than people who had no treatment, but the difference was too small to matter in everyday life.1
A Cochrane review of the trials found that, compared with placebo surgery, decompression does not improve pain, shoulder function or quality of life up to one year.3 For this reason, a proper trial of physiotherapy is advised before surgery is considered. Talk to your surgeon about what the operation can and cannot be expected to achieve in your case.
Risks of not having the surgery
Continued pain
Progression to rotator cuff tears
Complications
The cuts are very small, so complications are uncommon.
As with any surgery, there are some risks. They include:
- Problems with anaesthetic
- Shoulder stiffness
- Injury to nerves: The musculocutaneous and axillary nerves are the most at risk. Injury may cause pain or loss of feeling in the shoulder or forearm, or weakness in part of the arm. It is uncommon, and the effects are often temporary, though they may be permanent.
- Injury to bone: rarely, too much bone is removed from the shoulder
- Injury to the soft tissues in and around the shoulder joint: This may cause pain or instability in the joint. Again, the risk is low.
- Infection: Infection is a risk with any operation. But with the small cuts made in shoulder arthroscopy, infections are very rare.
- Damage to blood vessels: This is a very rare complication.
For more information on complications that can occur in any surgery, see Complications of Surgery.
Before the operation
Preadmission Clinic | Preparing for Surgery
Before your operation, you will be seen at the Preadmission clinic. This is to make sure you are fit for the operation and that all the tests you need are done.
During the visit, you will be seen by a
- doctor
- nurse
- anaesthetist (if necessary)
Tests
Tests that may be ordered for you include:
- Shoulder X-ray
- Shoulder ultrasound
- Shoulder MRI
- Blood tests
- ECG
Preparing Your Skin
Your skin should have no infections or irritation before surgery. If it does, contact your orthopaedic surgeon for a program to improve your skin first.
Tip
Carry a list of your medicines with you, with the name, dose and how often you take each one.
Medications
Your treating team will tell you which medicines to stop and which to keep taking before surgery.
Get some help from your friends and family
Recovery from this operation is usually quite quick, but you will not be able to use that arm well while it heals. You may want family or friends to help with daily tasks, such as cooking and driving, in the first week or so after the operation.
About the Operation
This is usually a day procedure. You come into hospital in the morning and go home the same day.
Subacromial decompression is done under a general anaesthetic, so you will not be awake. Local anaesthetic is sometimes used as well to reduce pain.
Usually only 2 cuts are needed, each no more than a few centimetres long. The surgeon puts the camera (arthroscope) in through one of them to check all the structures inside the joint. A burr is then used to remove about 4 mm of bone from the acromion. This is the part of the shoulder blade (scapula) that presses on the rotator cuff tendons.
When the operation is finished, the cuts are stitched closed.
After the Operation
After the operation you are cared for in the Theatre Recovery room. You will usually spend only 1 to 2 hours there.
Most people wake up fully once they are back in their room on the ward. The nurses will take care of you and check on your recovery often. It usually takes a few hours to recover fully from the anaesthetic.
What about pain?
At this stage the anaesthetic is still having an effect. Your ward doctors and nurses can give you more pain relief if you need it (see Post-Operative Analgesia), but arthroscopy is usually only mildly painful.
Recovery and Rehabilitation
You will be encouraged to start using the shoulder from day 1 after the operation. The exercises are passive and active assisted, and they move your shoulder in different directions.
The aim is full movement in your shoulder by 6 weeks. After this you will be encouraged to do strengthening exercises, building up to repeated overhead exercises 3 months after the operation.
F.A.Q.s | Frequently Asked Questions
What are the alternative treatments to having a Subacromial Decompression?
Most shoulder impingement gets better without an operation. Other things to try are:
- Physiotherapy. This is the main treatment and it works for most people. It builds up the rotator cuff and the muscles around the shoulder blade.
- Cutting back on jobs and sports that need a lot of reaching above your head
- Simple pain relief and anti-inflammatory medicine
- A steroid injection into the shoulder, which can ease the pain enough to let you do the exercises
Surgery is usually only considered after a proper try at physiotherapy lasting several months.
Are there important things I need to tell my doctors?
- Redness, swelling or warmth around the cut
- Leakage from the cut
- Fever and chills.
- Severe shoulder pain that is not relieved by prescribed painkillers.
- Further surgery planned for the future i.e. dental work, bladder catheterisation, examinations of the bowel, bladder, rectum or stomach.
References
- Beard DJ, Rees JL, Cook JA, Rombach I, Cooper C, Merritt N, Shirkey BA, Donovan JL, Gwilym S, Savulescu J, Moser J, Gray A, Jepson M, Tracey I, Judge A, Wartolowska K, Carr AJ. Arthroscopic subacromial decompression for subacromial shoulder pain (CSAW): a multicentre, pragmatic, parallel group, placebo-controlled, three-group, randomised surgical trial. Lancet. 2018;391(10118):329-338. doi:10.1016/S0140-6736(17)32457-1.
- Paavola M, Malmivaara A, Taimela S, Kanto K, Inkinen J, Kalske J, Sinisaari I, Savolainen V, Ranstam J, Järvinen TLN. Subacromial decompression versus diagnostic arthroscopy for shoulder impingement: randomised, placebo surgery controlled clinical trial. BMJ. 2018;362:k2860. doi:10.1136/bmj.k2860.
- Karjalainen TV, Jain NB, Page CM, Lähdeoja TA, Johnston RV, Salamh P, Kavaja L, Ardern CL, Agarwal A, Vandvik PO, Buchbinder R. Subacromial decompression surgery for rotator cuff disease. Cochrane Database Syst Rev. 2019;1(1):CD005619. doi:10.1002/14651858.CD005619.pub3.