
Adhesive Capsulitis
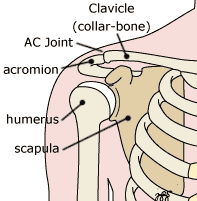
Frozen shoulder, also called adhesive capsulitis, causes shoulder pain and stiffness. It makes everyday tasks hard. Often no cause is found. It can follow a minor injury, surgery or a long time when the shoulder was not moved.
Every joint is wrapped in a joint capsule. The capsule keeps the joint stable and holds the lubricating (synovial) fluid inside. In frozen shoulder the capsule around the shoulder is too tight. This causes pain when you move and limits how far you can move the arm.
Symptoms
Frozen shoulder usually goes through 3 stages.
- Freezing phase: this first stage lasts about 6 months. It hurts to move the shoulder in any direction, and movement is limited.
- Frozen phase: the pain starts to ease, but movement is still limited in every direction.
- Thawing phase: the shoulder no longer hurts and movement slowly comes back.
Causes
The bones, ligaments and tendons of the shoulder sit inside a capsule of tough tissue. In frozen shoulder this capsule thickens and tightens around the joint, which limits movement.
Doctors are not sure why some people get it and others do not. It is more likely after the shoulder has been still for a long time, such as after surgery or a broken arm. Frozen shoulder is common in people with diabetes, so the immune system may play a part.
Risk Factors
The exact cause is not known, but some things raise your risk.
Age and gender
People aged 40 and over are more likely to get frozen shoulder. About 70 per cent of people who get it are women.
Immobility
People whose shoulder has been still for a long time are at higher risk. This can happen after:
Rotator cuff injury
Broken arm
Stroke
Recovery from surgery
Systemic diseases
Some medical problems raise the risk. These include:
Diabetes
Overactive thyroid (hyperthyroidism)
Underactive thyroid (hypothyroidism)
Cardiovascular disease
Tuberculosis
Parkinson’s disease
Investigations
Shoulder X-rays are often done to check for other causes of shoulder pain, such as arthritis. Your doctor may also order an ultrasound or MRI to look at the soft tissues in and around the shoulder.
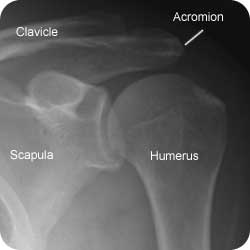
An X-ray of the Left Shoulder showing normal anatomy
Complications
Some people still have pain and stiffness for several years.
Treatment
Treatment aims to control pain and keep as much movement in the shoulder as possible.
Medications
Non-steroidal anti-inflammatory drugs (NSAIDs). These can ease pain and inflammation. Paracetamol can also help with pain.
Corticosteroids. An injection into the shoulder joint can ease pain and shorten the painful phase. Repeated injections are not recommended.
Allied Health
A physiotherapist can teach you exercises that keep the shoulder moving without causing a lot of pain.
Surgery
Distension. Sterile water is injected into the joint capsule to stretch it and make the joint easier to move.
Shoulder manipulation. You are put to sleep (general anaesthesia) and the doctor moves your shoulder to loosen the tight tissue.
Surgery. A few people need surgery, especially if symptoms do not improve with other treatment. Surgery removes scar tissue from inside the joint. It is usually done with keyhole surgery (arthroscopy), using a thin lighted tube passed through a small cut.
Looking After Yourself
Keep using the shoulder in daily activities as much as the pain allows. Heat or cold on the shoulder can ease pain.
Alternative Medicine
Acupuncture
Acupuncture uses extremely fine needles placed in the skin at specific points on the body. It has been used in China for thousands of years. The needles usually stay in for 15 to 40 minutes and may be moved during that time. The needles are thin and flexible and go in only shallowly, so most treatments are fairly painless.
Transcutaneous electrical nerve stimulation (TENS)
A TENS unit sends a tiny electrical current to points along a nerve pathway through electrodes taped to the skin. It is not painful or harmful. No one knows exactly how it works. It may trigger the release of natural pain relievers (endorphins) or block the pain signals carried by nerves.
Seeking Advice
Your Family Doctor (GP)
Your family doctor can diagnose your problem and help treat it. They can:
- tell you about your problem
- advise you of the best treatment methods
- prescribe you medications
- and if necessary, refer you to Specialists (Consultants) for further treatment
You will usually start with your GP, who may send you to a doctor who specialises in orthopaedics.
Bring along information about yourself
It helps your doctor if you bring:
- A list of your medications, including the name and dosage.
- Information about your medical problems and past treatment
- Previous investigation results, such as X-rays and blood tests.
Prepare a list of questions for your doctor
You may want to write a list that includes:
Detailed descriptions of your symptoms
Information about medical problems you’ve had
Information about the medical problems of your parents or siblings
All the medications and dietary supplements you take
Questions you want to ask the doctor
What to expect from your doctor
During the exam, your doctor may ask you to move your arm in certain ways to check for pain and how far you can move. These may include:
Hands up. Raise both hands straight up in the air, like a football player who has just scored a touchdown.
Opposite shoulder. Reach across your chest to touch your opposite shoulder.
Back scratch. Start with the back of your hand against the small of your back, then reach up to touch the opposite shoulder blade.
Your doctor may also ask you to relax while they move your arm for you. This helps tell frozen shoulder from a rotator cuff injury.
Your doctor may also check the nerves and muscles of your shoulder and arm by testing your:
Reflexes
Muscle strength
Muscle tone
Sensation
Prevention
One of the most common causes is a still, stiff shoulder during recovery from a shoulder injury, a broken arm or a stroke. If an injury makes it hard to move your shoulder, ask your doctor which exercises will stretch the tight capsule.
F.A.Q. | Frequently Asked Questions
How long does a frozen shoulder last?
On average 1 to 3 years, through a painful phase, a stiff phase and a thawing phase. Most people recover most of their movement, although a small loss of the end range can remain.1
Why did I get it?
Often no cause is found. It is more common between 40 and 60, in women, in people with diabetes or thyroid problems, and after a period when the shoulder was kept still, such as after surgery or a fracture.
What treatment helps?
In the painful phase, a cortisone injection into the joint eases pain and helps you keep moving. Physiotherapy helps most in the stiff and thawing phases. Pushing hard through pain early on does not speed recovery.
Will I need surgery?
Most people do not. If the shoulder is still very stiff after 6 to 12 months and interfering with life, options include stretching the joint with fluid under X-ray guidance (hydrodilatation), moving it under anaesthetic, or keyhole surgery to release the tight capsule.
References
- Hand C, Clipsham K, Rees JL, Carr AJ. Long-term outcome of frozen shoulder. J Shoulder Elbow Surg. 2008;17(2):231-236.